


Five years. For more than five years now, I have been trying to understand in detail why and how the COVID vaccines have harmed - and are still harming - our friends and families.
Those who follow the Bolus Theory know that it outlines most of the causes and contributing factors of the observed adverse reactions.
There are very few conjectures in the work, and all are grounded in robust logic and scientific laws. Nonetheless, some areas of the theory still need validation, notably by confirming educated conjectures about the white clots.
Today, I want to build on the fantastic work conducted by two scientists in New Zealand, Bruce Rapley and Matt Sheldon, who produced a remarkable scientific trilogy, three papers on white clots:
one on their physical characteristics1,
one on their chemical components2, and
one on their protein content3.


Even though their research didn’t position the white clots within the dynamics of the Bolus Theory framework, you’ll see that their findings align extremely well with what I have been saying for over two years, vindicating the Bolus Theory and observation-based hypotheses I had put forward, and provide further depth to our understanding. Though it’s a bit technical, anyone can understand. I hope you’ll enjoy.
I remember the first time I heard about white clots. We were on Steve Kirsch’s Thursday scientific committee call with Jessica Rose and a few other pro bono scientists Steve had recruited. I believe it was four years ago, February 2022.
Let’s be honest, no one on the call had a clue what these white clots, extracted by embalmers from recently deceased, were.
The synchronicity with the vaccination program was evident, pointing to the COVID vaccines. Wild conjectures started floating around.
To me, these white clots further confirmed that the focus should be on the damage the vaccine particles were causing to the lining of blood vessels. After all, once in the circulatory system, the LNPs were essentially trapped in a closed loop, and we were seeing the signs of considerable endothelial damage.
At the time, few wanted to consider the danger of having billions of particles circulating in the vascular system, telling the immune system to destroy all contaminated cells… Most were focused on where the lipid nanoparticles were going rather than where they circulated, as if our vasculature were unimportant.
Given lipid nanoparticles’ nature, the blood flow momentum would inevitably push the LNPs onto the lining and facilitate transfection there, much more so than in idle immobile storage inside muscle tissue or in any form of a biological sack. Observations showed that’s where things were happening.
Since I had learned a few months before that the vaccine particles didn’t stay in the muscle but leaked into the circulatory system, I followed that lead tenaciously, and haven’t stopped to this day.
My thinking was that doctors a century ago must have had a good reason to invent and generalize the aspiration technique… moreover, why would public health authorities in Denmark and Hong Kong change the injection protocol to reinstate the aspiration technique4 if the intravenous risk didn’t exist? (Germany would do the same in Feb 2022)
In early September 2021, I had read a study from Hong University5 that reproduced, in mice, the same adverse reactions we were seeing in the vaccinated population: necrosis, lymphocyte inflammation, and calcification in the heart and liver. I shared the study widely. To my surprise, in the medical freedom movement, nobody cared…nothing had changed since Semmelweis.
Calcification
A first hypothesis appeared on my whiteboard: could calcification be at play, as in the hearts of these mice? Calcification was falsified at a later stage when I spoke to the embalmer, Richard Hirschman, who clearly observed that the clots weren’t calcified. Too flexible and elastic, very distinct from calcified plaques.

Long concentrated denudation of arterial linings ✓
Another fact-rooted conjecture followed immediately: Could longitudinal harm to the arteries’ walls, caused by concentrated T-cell attacks, be the root cause of these white clots? (that’s been confirmed, validated, and explained notably by my most recent simulation work)
Vaccines in IV trigger abnormal coagulation (thrombosis) ✓
I had also discovered another study6 from a university in Munich in which mice were injected intravenously, this time with the AstraZeneca vaccine, and thromboses were repeatedly stimulated.
Again, nobody cared.
As almost everyone focused on spike protein toxicity, I was left to pursue this scientific quest to make sense of vaccine accidents and understand the different circumstances. But one pathological process ended up being harder to crack than others: white clots.
Abnormal, but Natural
When writing “The Needle’s Secret”, I conjectured that the white clots were natural clots formed in abnormal conditions.
The fact that this phenomenon was supposedly new (it wasn’t; I found an article from 1947 mentioning a white clot) didn’t mean that white clots weren’t part of a natural process. The white clot wasn’t calcifying despite the lack of endothelium; this couldn’t be a random process. This was a natural process formed in an abnormal context, or in circumstances we couldn’t yet understand.
Everything pointed to the considerable damage inflicted to the endothelium. In an article on thrombosis, I used the “thousand cuts” analogy7 that was an understatement.
It is well established that high-flow arteries resist clogging, as evidenced by the fact that arterial hemorrhages do not cease naturally. The blood flow in the lumen, the central part of the artery, will instantly push away any clot buildup. That explains the shape of elongated Life Savers (or small donuts) with a hole in the middle, in which blood continues to circulate for years.

Coagulation had attached to the stripped linings of the arteries, but the power of the blood flow at the center of the artery pushed aside - or away downstream (deep vein thrombosis) - the coagulated elements, just as a powerful river carves its way down a mountain.
Once again, this is simple physics at play that everyone can understand and explain.
Immune Cells Hollowing Out the White Clots
If the clot mysteriously persisted, the immune system would certainly not remain idle in the meantime and leave unprocessed material inside.
Immune cells would unequivocally infiltrate and roam this white mesh to process whatever needed to be processed, notably cellular debris and residual proteins.
White and red blood cells, along with debris of destroyed endothelial cells (NB: the trigger of coagulation is the destruction of endothelial cells) would have inevitably been caught in the fibrin mesh during the coagulation cascade. Neutrophils and macrophages would then naturally process cellular debris and spike proteins stuck in white clots, whenever accessible, very progressively, layer by layer.
That reality was confirmed by:
The white color of the clots (the red color of clots comes from the red blood cells, the erythrocytes, the change in color means they died and were processed out),
Some vaccinated expressing high levels of anti-spike antibodies (spike proteins stuck in the clot would trigger antibodies, but the small number doesn’t use them up), and
The hollowed-out fibrinous structures discovered by microscopic photographs of the white clots8, resembling a hollow 3D-printed structure when the soluble product is dissolved.

Studies conducted in 2025 revealed neutrophil infiltrations9, confirming that a cleanup process was at play. In other words, the white clots are the outcome of multiple dynamics: first, extraordinary damage to the endothelium, then an overwhelming abnormal demand for coagulation (and repair), and then the slow progressive 24/7 clean-up work of anything it can access inside this clot.
Tiny Dissolution Signal
By reverse-engineering the clot dissolution process, I realized the maths didn’t work.
The long morphology of the clot (as opposed to normal cross-sectional harm) would inevitably mean that the dissolution signal (tPA: plasmin activator), sized for a “tiny” cross-sectional cut, would be minuscule and insufficient relative to the 25cm-long clot.
The signal sent by neighboring cells would be proportional to a cross-section of a 1 cm diameter artery or 2,380 cells! That’s roughly 10,000x less than needed (25cm length/25μm length of an endothelial cell=10,000x).
In other words, everything else being equal, if it takes 2 hours to dissolve a normal cross-sectional clot, the clot should have disappeared after 2 years and a quarter. That’s evidently part of what’s going on, but many people died 2 years post-vaccination and still had quite large white clots. So here, honestly, I must admit I missed something, mea culpa. I just had half of the picture.
I should have realized something else was at play. The circulating microclots were a hint that I missed (i.e. why wasn’t the dissolution at the molecule level? why were they breaking up in such large blocks?).
And the White Clot Trilogy brings a new fundamental piece of information: the lack of plasmin inside the clot.
Again, it’s all about imbalances in coagulation factors.
Imagine an extraordinary request for coagulation elements; some would inevitably be depleted. We know when platelets are depleted, it’s called thrombocytopenia. What is it called when plasmin is missing? Plasminopenia?
What happens when plasminogen found in the blood is depleted locally?
If, inactivated plasmin is not disseminated enough and regularly throughout the blood clot, the dissolution of the clot will not happen molecule-by-molecule, but in irregular clusters of fibrin…nobody can dispute that.
Rapley and Shelton found that plasmin was present at a level 4 times lower than normal.
Two immediate consequences come to mind:
Circulating plasmin activators (independently of stricter mesh density) would take 64 times longer (4^3) to find a plasmin molecule. Why? This is similar to a party in a multi-floor place where you can spend the whole evening trying to find your friends.
Now, we understand why these clots are frozen in time: With the combined levels of tPA (dissolution activators) stimulated by the abnormal wound topology and the plasmin repair depletion, it would take 146 years for the clot to dissolve!10The second consequence is that when dissolution happens, blocks get separated, not molecules of fibrin. On average, these blocks would be 64 times bigger than normal, likely with considerable variability depending on the area.
Finally, we understand where the microclots come from and why they vary in size: during coagulation, the concentration of plasmin in the blood fluctuates as available plasmin is consumed, and there is likely considerable variability across layers.
And indeed, several studies, seemingly independent of white clots, identified white microclots circulating in the bloodstream1112. These fibrinous elements were relatively small but not small enough13 to circulate freely in the vascular system without getting stuck in capillaries.
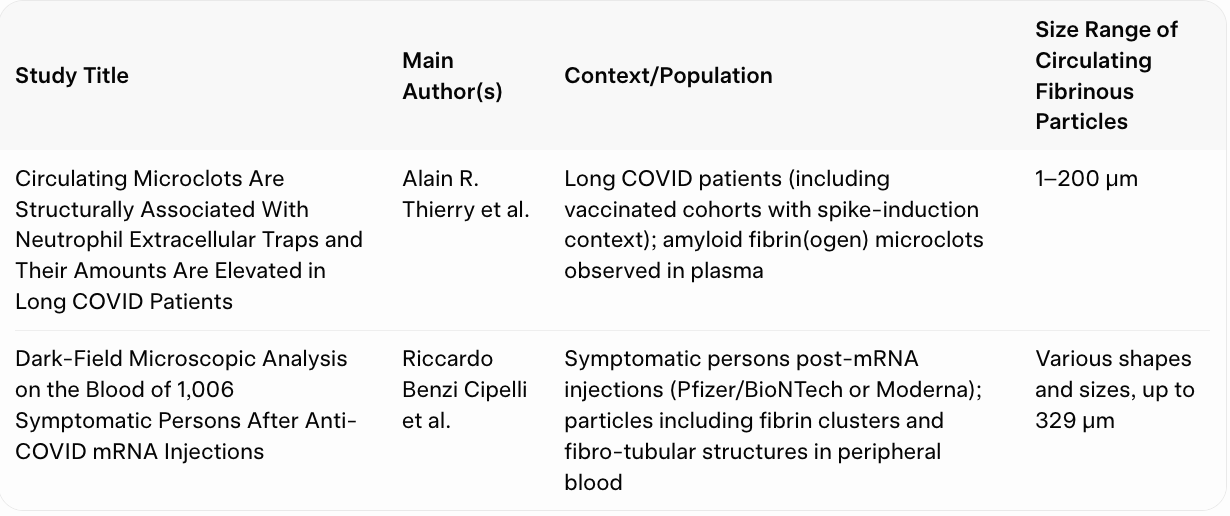
This means that the presence of fibrin elements has to be very recent. Many, without a clear biological process, jumped to the conclusion that misfolded proteins crystallized in the blood, the infamous amyloid boogeymen, and continued on end for years.
The hypothesis I propose/d - I believe a more rational hypothesis and now perfectly justified - is confirmed:
Elements of white clots break off progressively as the immune system cleans up the fibrin mesh and irregularly placed plasmin is activated.
A Denser Fibrin Mesh
In their Trilogy, Rapley and Shelton found that normal proportions of the fibrin components (Alpha-Beta-Gamma chains) were repeatedly skewed in the same way (i.e. not a random process). The share of Alpha-chains is normally equal to the Beta and Gamma: 1:1:1. They found 1:7:3.
They didn’t explain the difference, but suggested that it could explain the tighter density of the white clots. Their conjecture is that this proportion was different when the clot formed. The problem with that hypothesis is that fibrinogen chains are formed and liberated synchronously and bound. For the bounds to be broken prior to coagulation would require very high concentration enzymes to circulate in the bloodstream, or at the point of location, which is difficult to imagine.
I want to propose a different hypothesis on this imbalance that matches the Bolus Theory. In their analysis of the clots, Rapley and Shelton found significant presence of enzymes ( myeloperoxase and Cathepsin G ) inside the mesh that would more easily explain break-up of the Alpha and Gamma-chains. In other words, as the immune cells progress inside the clots and clean up, parts of the fibrin mesh are more easily broken away than others because they are more accessible.
I also want to propose a different evidence-based explanation for fibrin density and elasticity, again related to repair imbalances.
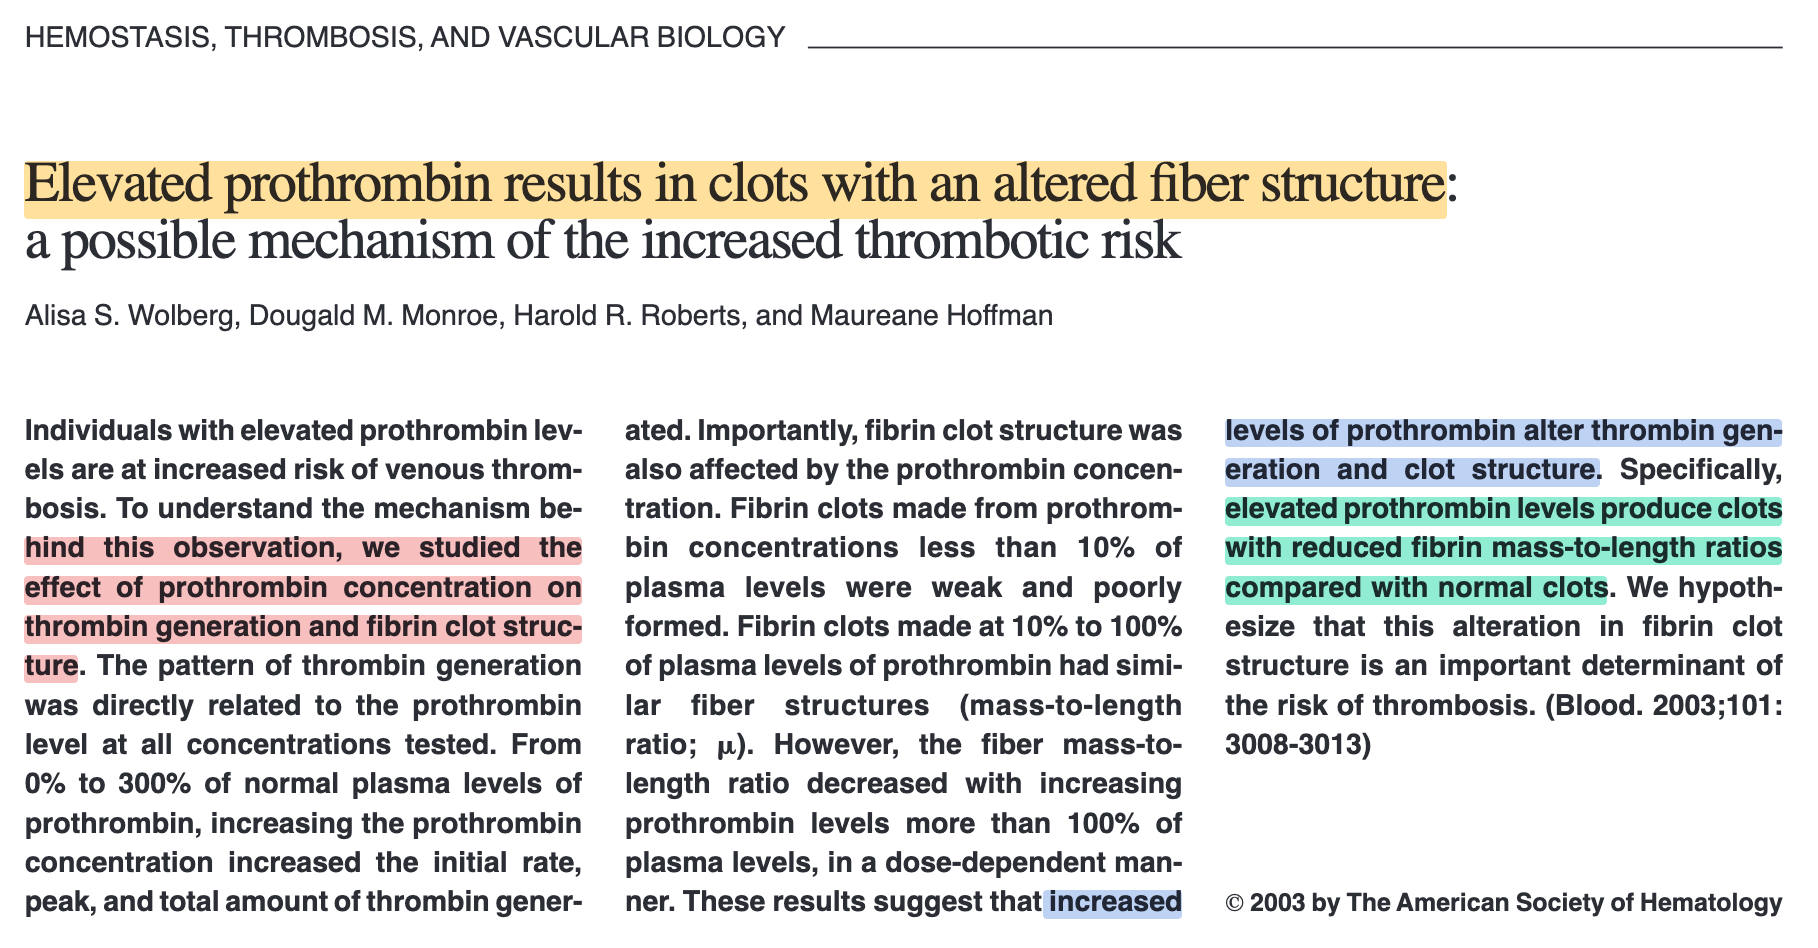
We’ve already proven that the demand for coagulation is very intense. There is repeated evidence from multiple experiences141516 that when too much thrombin is expressed during the coagulation cascade, the density of the clot is changed, namely, the fibers are shorter and thinner, making a denser abnormal clot with smaller pores, less entrapment, and a more elastic behavior.
Thank you for following me all this long. Now, we have most of the mystery of white clots revealed: white clot form, behavior, location, persistence, composition, etc…
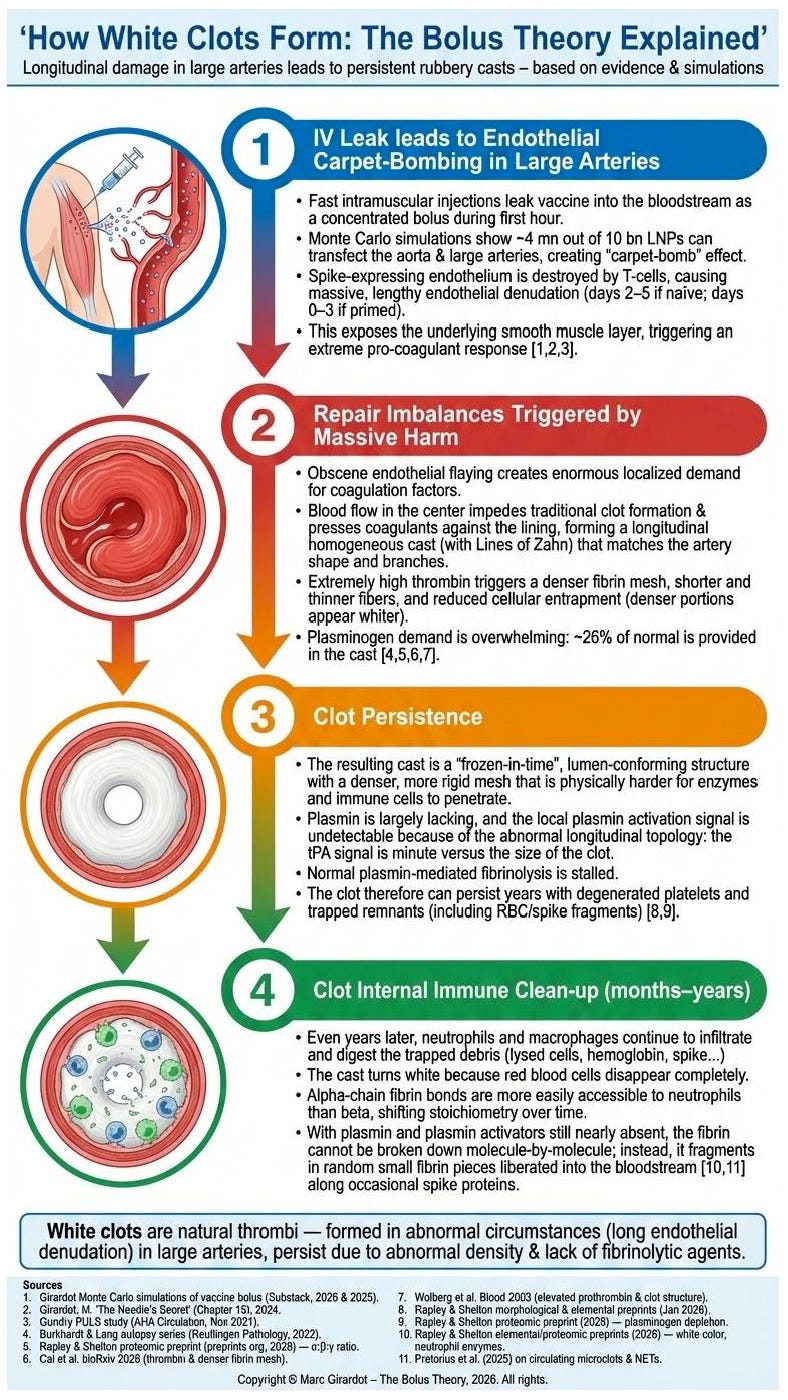
I created the above infographics for you.
Block 1 – The Trigger: IV Bolus and Long Endothelial Denudation in Large Arteries
An inadvertent intravenous delivery sends lipid-nanoparticle-filled with mRNA straight into the venous return. My Monte Carlo simulations show roughly 4 million endothelial cells transfected, concentrated along the 1–2 metres of aorta and large arteries — the exact zone of highest pulsatile flow. Cytotoxic T-cells, primed after the second dose (Ogata and Yonker kinetics), strip 20–40 cm² of intima in long patches. This is the longitudinal topology I highlighted in “The Needle’s Secret” two years ago: the damage is not a small cross-sectional wound; it is square centimeters of endothelial surface area distributed linearly. The endothelium that normally secretes tissue plasminogen activator (tPA) right where it is needed is gone. That single fact sets the stage for everything that follows.
Block 2 – Repair Imbalances Triggered by Colossal Endothelial Harm
The sheer scale of the injury triggers an over-supply of thrombin. Multiple studies (now confirmed in my personal files) show that the more intense the thrombotic burst, the denser the fibrin mesh becomes, with thinner individual fibres. This density explains both the rubbery hardness everyone notices and the reduced cellular entrapment — exactly like the final plastic scaffold after the soluble supports are washed away. The dense matrix also physically blocks later penetration by enzymes and immune cells. Another instantiation of repair imbalance: the body throws everything it has at the leak, but the intensity creates a structure that is now harder to clear.
Block 3 – The Triple Lock of Persistence: Why the Cast Refuses to Dissolve
This is the heart of the story and the exact conclusion of my 4-block infographic:
“White clots are normal thrombi, formed in abnormal circumstances (long endothelial denudation) in large arteries, persist due to abnormal density and lack of fibrinolytic agents.”
Three mechanisms lock the sleeve in place:
Complete local loss of tPA production — the endothelium that should release it at the site is destroyed.
Severe plasmin depletion inside the clot. Normally, inactivated plasmin makes up about 0.5 % of clot proteins. Here it is around 0.13 % — roughly one-quarter the normal amount. In a 3D environment that translates to approximately 64 times slower dissolution even if tPA were present.
The abnormally dense mesh physically limits access for whatever fibrinolytic enzymes and immune cells do arrive.
Rapley & Shelton’s proteomic deep-dive lands here like a thunderbolt: plasmin measured at just 0.128 %, abnormal stoichiometry between alpha, beta and gamma fibrin chains, a hybrid matrix, and — most tellingly — no spike protein dominance in the top proteins. These are natural clots, not foreign invaders.
Block 4 – Contextual Clean-Up: The Immune Crew Moves In
Only after the triple lock is fully explained do we see the secondary process that everyone has been photographing. Macrophages and neutrophils invade the cast with enzymes. They methodically wash away the “soluble supports” (RBCs, WBCs and other trapped material) — explaining the whiteness and the hollowed scaffold. Small fragments break off and circulate briefly before being caught by the liver or capillaries. The depletion of alpha and gamma chains is the direct signature of this neutrophil-driven proteolytic work — not failed polymerisation or any cross-reaction. The immune system is doing exactly what it is supposed to do inside a persistent scaffold: cleaning house.
A Masterpiece That Fits the Bolus Picture Perfectly
Drs Bruce Rapley and Matt Shelton (together with NZDSOS) have produced a rigorous, multi-continent three-paper tour de force — morphology, elemental analysis, and now this proteomic deep-dive (preprints202601.2319.v1 and its two companion papers). Their data are clean, reproducible and honest. They have given the world the clearest picture yet of what these clots actually are at the molecular level. I want to thank them.
Their excellent work leaves open exactly the upstream and temporal gaps that the Bolus framework closes: the root cause (IV-induced bolus), the months-to-years time lag between formation and analysis, the sheer longitudinal scale of endothelial destruction, the intensity-driven repair imbalance, and the active (but secondary) immune hollowing process. They did a fantastic job. The missing context was never their brief — and now it slots in perfectly.
Another flawless block added to the Bolus edifice. My two-year-old prediction of tPA insufficiency caused by longitudinal topology is now proven at the protein level. These are not alien, or mysterious structures. They are normal thrombi formed in abnormal circumstances whose persistence is fully explained by density plus fibrinolytic failure.
The circulating micro-elements that once alarmed people are not accumulating poison, not misfolded proteins — they are bits of the fibrin mesh being washed away.
I rest my case. I hope you found this insightful and will support my work and my family.
Have a beautiful Sunday.
Marc

“Morphological and Histological Characterisation of Anomalous Intravascular Casts (AICs)” by Bruce Rapley & Matt Shelton - Reference
“Elemental Characterisation ofAnomalous Intravascular Casts Revealsan Abnormal Biochemical” by Bruce Rapley & Matt Shelton - Reference
“Proteomic Characterisation of Anomalous Intravascular Casts Reveals Non-Canonical Fibrin Architecture and Impaired Fibrinolysis” by Bruce Rapley & Matt Shelton - Reference
The aspiration technique refers to the procedure whereby the injector, after having inserted the needle in the muscle, pulls on the syringe plunger to check for blood to avoid direct injection in the circulatory system. However, this technique is no panacea, as it does not prevent direct leakage via small severed capillaries.
Effectively, aspiration gives a false sense of safety.
“Intravenous injection of COVID-19 mRNA vaccine can induce acute myopericarditis in mouse model“ by Li et al. - Reference
“Thrombocytopenia and splenic platelet directed immune responses after intravenous ChAdOx1 nCov-19 administration” by Nicolai et al. - Reference
“Could the Geometry of Blood Vessel Wounds Be the True Trigger Behind Vaccine-induced Thrombosis?” by Marc Girardot - Reference
“Whole-Genome Sequencing of Fibrin Clots (“Calamari” Amyloidogenic Aggregates)” by Kevin McKernan Ph.D. - Reference
It’s likely that circulating plasmin activators from other injuries or bleeding in the body throughout the years contribute to and accelerate this process.
“Circulating Microclots Structurally Associated with Neutrophil Extracellular Traps (spike-induction context)” by Pretorius et al. - Reference
“Dark-Field Microscopic Analysis on the Blood of 1,006 Symptomatic Persons After Anti-COVID mRNA Injections” by Benzi Cipelli et al. - Reference
Indeed, the diameter of a capillary being roughly 10 micrometers (1/millionth of a meter), anything bigger would get stuck rapidly, either in the organ capillaries, causing micro-thromboses, or in the filtration organs, notably the liver.
“Elevated prothrombin results in clots with an altered fiber structure: a possible mechanism of the increased thrombotic risk '“ by Wolberg et al. - Reference
Please read the article and comment based on the article's content. Thank you.
How I wish that farseeing investigators like you didn't have to suffer insults and incredulity for years before being vindicated.